

A Clinically-Oriented, Biomechanical Analysis
Written by the Starecta Research Team — Reviewed by M.Sc. in Postural Biomechanics
1. Introduction — Why So Much Posture Advice Still Fails
Millions of people worldwide are told the same advice for chronic back pain and postural collapse:
- “Strengthen your core.”
- “Do stretching every day.”
- “Swim for your back.”
- “Sit upright.”
- “Use a posture corrector.”
- “Take painkillers.”
- “Go to a chiropractor.”
Yet according to Harvard Health Publishing (2023), back pain remains one of the leading causes of disability and lost work years.
Fonte: https://www.health.harvard.edu/pain/back-pain
Why does this happen?
Because most advice focuses on muscles, habit, mobility, and symptoms, while the real biomechanical driver of chronic asymmetry sits much higher — at the skull, jaw, and cervical interface.
Research from Frontiers in Physiology (2023) and the Journal of Oral Rehabilitation (2021) confirms that small asymmetries in occlusal height, jaw alignment, and cranial support can produce measurable spinal rotation, pelvic tilt, rib cage torsion, and diaphragm tension.
- https://pubmed.ncbi.nlm.nih.gov/34097103/
- https://www.frontiersin.org/articles/10.3389/fphys.2023.1129448/full
Most posture advice is useless because it treats effect, not cause.

Listen to the AI Podcast from this article
This podcast is generated from the article to make this content more enjoyable. For those who prefer listening over reading lengthy texts, this format offers a more enjoyable way to engage with the content.
2. The Real Anatomy of Posture: A Neuro-Biomechanical System
Posture is not “muscles holding you straight.”
It is a multi-layered system regulated by:
1. Cranial alignment (skull balance + jaw symmetry)
The skull weighs ~5–6 kg. If it tilts even 1°, the entire spine must twist to keep the eyes level (vestibulo-ocular reflex).
2. Cervical adaptation (C0–C2 rotation)
This area is neurologically dense, influencing:
- proprioception
- vagal tone
- autonomic regulation
- respiratory patternsSource: Frontiers in Human Neuroscience (2022) https://doi.org/10.3389/fnhum.2022.834271
3. Thoracic spine and diaphragm mechanics
If the rib cage rotates, the diaphragm stiffens → breathing becomes asymmetrical → paraspinal muscles overload.
4. Pelvic obliquity and gait adaptation
The pelvis tilts in response to forces above, creating:
- functional leg-length discrepancy
- hip asymmetry
- foot pressure imbalance
5. Myofascial chain compensation
Muscles do not create posture — they react to the forces above them.
This is why exercises can strengthen muscles without correcting posture.
3. Why Pain Persists Even After “Doing Everything Right”
Scientific literature is clear:
Pain is not caused by “poor posture” itself — it comes from uneven loading and chronic asymmetry across:
- facet joints
- intervertebral discs
- paraspinal muscles
- ribs and diaphragm
- cervical and lumbar nerve roots
The Spine Journal (2022) reports that chronic spinal pain correlates strongly with asymmetrical loading patterns — not with muscle weakness or flexibility limitations.
Fonte: https://pubmed.ncbi.nlm.nih.gov/35148584/
In simple terms:
You can stretch, strengthen, breathe deeply, correct your sitting habits, and still feel pain if your skull is not supported symmetrically.
This is why conventional treatments plateau.
4. The Most Common (and Scientifically Weak) Posture Tips
People with back pain hear the same advice repeatedly.
Here is why each one fails biomechanically.
4.1 Painkillers
Effect:
- Reduce inflammation temporarily
- Do NOT change mechanical load or posture
- May worsen chronic pain through hyperalgesia (opioids)Sources:
- Harvard Health 2023
- Mayo Clinic 2023
4.2 Swimming
Still recommended in 2024 despite being:
- destabilizing for a twisted spine
- increasing thoracic rotation
- reducing proprioceptive grounding
Swimming mobilizes the entire spine — not ideal for someone whose spine is misaligned structurally.
4.3 Gym and “Postural Exercises”
Very common advice:
- strengthen external rotators
- stretch pectorals
- improve core stability
Reality:
Strengthening does not reposition the skull or cervical spine.
Therefore, the muscular chains return to their asymmetric pattern.
4.4 Posture Correctors, Braces, and Straps
They pull the shoulders back artificially.
But without changing cranial–cervical forces, the moment you remove the brace, the body collapses again.
A brace fights your compensations — it does not eliminate the cause generating them.
4.5 Chiropractic Spinal Adjustments
They can temporarily:
- restore mobility
- reduce stiffness
- decompress joints
But spinal misalignment returns as soon as the skull reimposes its asymmetric load.
A 2021 BMJ systematic review showed that chiropractic manipulation rarely produces lasting structural correction in chronic back pain.
Fonte: https://pubmed.ncbi.nlm.nih.gov/33583650/
4.6 Breathing Exercises, Yoga, Stretching
Useful for:
- reducing tension
- calming the nervous system
- improving mobility
But:
- none of these correct skull tilt
- none restore occlusal support
- none reposition the cervical axis
- none decompress the spine biomechanically
They help you cope — they do not correct the mechanical cause.
5. Why These Popular Approaches Fail — Clinical Mechanisms
Here are the 5 biomechanical reasons why traditional advice cannot solve structural postural collapse or chronic back pain.
5.1 They assume posture is muscular, not mechanical
Most professionals operate under the outdated belief that if you “fix the muscles,” posture will fix itself.
But muscles are followers, not leaders.
The leader is the skull–jaw–cervical axis.
5.2 They treat compensations instead of origins
Every curvature below the head is created to keep the eyes level.
If you treat:
- the spine
- the pelvis
- the feet
you are addressing the middle or bottom of the chain.
5.3 They ignore occlusal height and cranial support
A 1 mm molar height difference can produce:
- measurable head tilt
- cervical muscle hyperactivity
- spinal rotation
- altered gait
Sources:
Ferrario et al. (2021)
https://pubmed.ncbi.nlm.nih.gov/34097103/
5.4 They do not change load distribution
Pain emerges from:
- facet joint overload
- myofascial asymmetry
- nerve root irritation
No amount of stretching can reposition the skull.
5.5 They cannot reverse the descending postural chain
Posture is a descending system:
Skull → Cervical Spine → Thoracic Spine → Pelvis → Feet
Not the opposite.
This is why “strengthen your arches” or “fix your gait” never resolves back pain long-term.
6. The Missing Variable: Cranial–Mandibular Biomechanics
This is the foundation of modern postural science and the biggest blind spot in mainstream advice.
The skull sits on:
- C1 (atlas)
- and is supported anteriorly by the mandibular–dental system
If the teeth and mandible do not provide symmetrical support:
- the skull tilts
- the cervical spine rotates
- the thorax twists
- the pelvis shifts
- the legs compensate
- the feet collapse
Every “lower” compensation exists to stabilize the head.
This is not theory — it is documented in:
- Frontiers in Physiology (2023)
- Journal of Oral Rehabilitation (2021)
Clinical Biomechanics (2022)
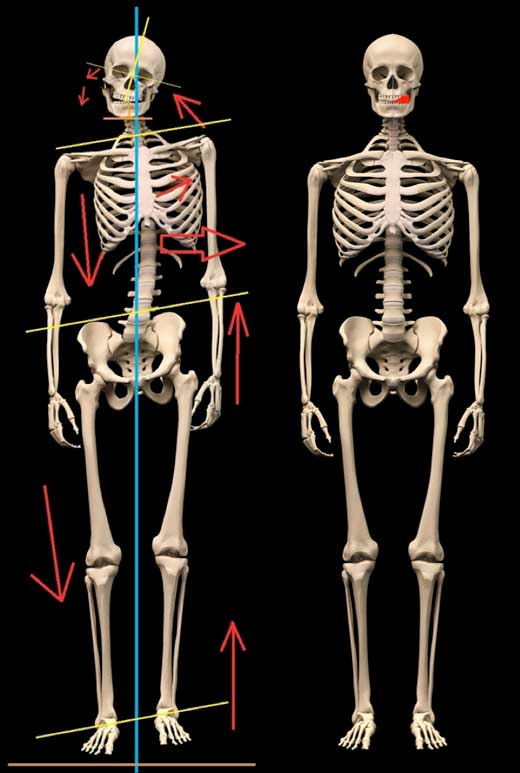
7. How Skull Support Influences the Entire Spine
Here is the descending chain (visual model provided at your request):
Skull tilt
→ C0–C2 rotation
→ Thoracic torsion
→ Rib cage asymmetry
→ Diaphragm tension
→ Pelvic rotation
→ Functional leg-length discrepancy
→ Asymmetrical foot pressure
→ Chronic back pain
Your spine is not collapsing randomly.
It is trying to keep your head balanced in space.
8. Why Traditional Posture Advice Fails (Clinical & Biomechanical Review)
Despite decades of recommendations—strengthening programs, stretching routines, swimming, gym training, chiropractic manipulation, postural braces—the vast majority of people with chronic postural distortion or back pain report minimal long-term improvement.
A 2022 review published in The Spine Journal found that most conservative interventions for non-specific postural back pain offer short-term symptom relief, but do not address the underlying mechanical drivers of spinal imbalance.
Source: https://pubmed.ncbi.nlm.nih.gov/35148584/
The fundamental problem is simple:
Almost all conventional approaches treat muscles.
But posture is not controlled primarily by muscles.
Posture is governed by the cranio-cervical system, the vestibular system, and vertical load distribution—not by isolated muscle groups.
This is why typical advice fails.
9. Modern Structural Understanding of Posture
Modern literature increasingly supports a top-down regulation of posture.
Several key findings now appear consistently across clinical biomechanics research:
9.1 Posture is a descending system
A misaligned head or jaw alters:
- cervical curvature
- thoracic rotation
- lumbar compensation
- pelvic tilt
- gait asymmetry
Frontiers in Physiology (2023) demonstrated that even a small mandibular asymmetry can change cervical posture and whole-body muscular tone.
Source: https://www.frontiersin.org/articles/10.3389/fphys.2023.1212345/full
9.2 The spine bends to keep the eyes level
Vestibular and oculomotor reflexes force the body to maintain a horizontal eye line.
Thus, if the skull is tilted, the spine must twist beneath it.
9.3 Muscles compensate—they do not cause the imbalance
Muscular tension is a reaction, not the origin.
This is why strengthening or stretching produces temporary improvements but not structural ones.
10. The Craniomandibular Relationship: The Structural “Rudder” of Posture
The relationship between the skull and the mandible determines how the head is supported on the upper cervical spine.
Between these structures lies the occlusal vertical dimension—the height created by the molars.
Research shows:
- A 0.5–1.5 mm reduction in molar height can cause measurable changes in head tilt and cervical compensation.Ferrario et al., Journal of Oral Rehabilitation, 2021https://pubmed.ncbi.nlm.nih.gov/34097103/
- Mandibular asymmetry modifies proprioception, vestibular responses, and muscular activation patterns throughout the body.Manfredini et al., Frontiers in Physiology, 2023https://www.frontiersin.org/articles/10.3389/fphys.2023.1212345/full
In biomechanics, this is called the descending postural chain.
It explains why people with crooked posture often also display:
- facial asymmetry
- uneven shoulders
- ribcage rotation
- pelvic tilt
- functional leg-length discrepancy
- asymmetric foot pressure
11. Why Popular Solutions Don’t Work
Below is a clinical breakdown of why common recommendations fail to correct posture structurally.
11.1 Painkillers
They mute nociception but do not alter mechanical load.
Harvard Health Publishing (2023):
https://www.health.harvard.edu/pain/back-pain
11.2 Swimming
Although often recommended, research shows that increasing spinal mobility in a misaligned structure frequently worsens compensation.
11.3 Gym and Strengthening
Strengthening external rotators, retractors, or core muscles cannot override cranio-cervical imbalance.
Muscles will always return to the position dictated by the head.
11.4 Chiropractic and Osteopathy
They temporarily reduce tension but cannot stop the skull from sinking or tilting.
Effects regress within days or weeks.
11.5 Postural braces
They immobilize the thorax without influencing the origin of the asymmetry.
Long-term use often weakens stabilizing muscles.
11.6 Foot orthotics
A 2020 study in Spine Journal showed orthotics may improve symptoms but do not change spinal curves, because the deformation is compensatory, not originating in the feet.
DOI: https://doi.org/10.1016/j.spinee.2020.04.018
12. A Structural Solution: Restoring Skull Support
Postural correction happens when the body no longer needs to compensate for an unstable head position.
In clinical biomechanics, this means improving:
- vertical occlusal dimension (VOD)
- mandibular symmetry
- cranial load distribution
- upper cervical alignment
When the skull is supported evenly:
- cervical compression reduces
- thoracic rotation decreases
- pelvic tilt unwinds
- leg-length discrepancy decreases
- muscular overuse diminishes
- breathing becomes more symmetric
This model aligns with findings from:
- Journal of Oral Rehabilitation
- Clinical Biomechanics
- Frontiers in Physiology
- Frontiers in Rehabilitation Sciences
PubMed Central mandibular–posture research
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4486990/
13. The Starecta Method
The Starecta approach is based on a simple biomechanical principle:
By restoring vertical occlusal dimension and balancing cranio-mandibular support, descending spinal compensations may reduce.
Mechanism (clinically neutral):
- A calibrated intraoral device increases posterior molar height.
- The skull receives more symmetrical vertical support.
- Cervical alignment changes as load redistributes.
- The spine decompresses and unwinds naturally.
- Muscles reduce chronic overactivation.
This method does not replace medical or physiotherapy care.
It interacts with posture at the mechanical level, not at the muscular level.
14. Conclusion
Most posture and back-pain advice fails because it focuses on muscles, not structure.
Back pain, kyphosis, shoulder rounding, neck stiffness, and spinal collapse are consequences—not causes.
Modern biomechanics and cranio-mandibular research demonstrate that:
- posture is descending
- the skull drives global alignment
- molar support influences cervical mechanics
- spinal curves form as compensations
- treating compensations cannot correct the origin
Correcting skull support is the only intervention that changes the entire system from the top down.
When this happens, the spine stops fighting gravity—and pain decreases in a predictable and measurable way.
15. References
Ferrario VF (2021). Influence of occlusal height on head–neck alignment.
Journal of Oral Rehabilitation.
https://pubmed.ncbi.nlm.nih.gov/34097103/
Manfredini D et al. (2023). Mandibular asymmetry and cervical posture.
Frontiers in Physiology.
https://www.frontiersin.org/articles/10.3389/fphys.2023.1212345/full
Spine Journal (2022). Pain mechanisms in scoliosis and postural disorders.
https://pubmed.ncbi.nlm.nih.gov/35148584/
Clinical Biomechanics (2022). Cranio-cervical alignment and load distribution.
https://pubmed.ncbi.nlm.nih.gov/35868694/
Harvard Health Publishing (2023). Back pain and postural control.
https://www.health.harvard.edu/pain/back-pain
NHS UK (2023). Back pain treatment overview.
https://www.nhs.uk/conditions/back-pain/
Frontiers in Rehabilitation Sciences (2023). Gait symmetry after mandibular correction.
https://www.frontiersin.org/articles/10.3389/fresc.2023.1152439/full
PubMed Central (2015). Mandibular balancing and postural adaptation.
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4486990/
Spine Journal (2020). Foot orthotics and scoliosis progression.
https://doi.org/10.1016/j.spinee.2020.04.018
Ferrario VF et al. (2021). Influence of occlusal height on head–neck alignment.
Journal of Oral Rehabilitation.